Emergency discomfort is not tidy. It shows up in layers, shaped by physiology, concern, context, and the clock. I have seen a tranquil young adult grit teeth through a fractured span, and an older male spiral from a straightforward hip fracture right into ecstasy due to the fact that his discomfort was undervalued and undertreated. PUAEME008, the national device generally known as Offer Discomfort Management, exists to shut that gap in between concept and the bedside. When instructed and used well, it gears up medical professionals and responders to bring alleviation rapidly, safely, and consistently.
This is not nearly pushing anesthetics. It is about structured analysis under stress, choosing the best modality for the patient in front of you, and having the functional self-control to paper, hand over, and testimonial. If you are checking out a pain monitoring course, whether as part of prehospital training or a hospital-based upskill, recognizing exactly how PUAEME008 plays out in the area aids you pick sensibly and practice with confidence.
What PUAEME008 actually covers
On paper, PUAEME008 Give Pain Management establishes performance requirements around analyzing pain, administering authorized analgesia, monitoring feedbacks, and connecting effectively with getting teams. In technique, the system is a scaffold for judgment. It requires you to integrate medical pattern acknowledgment with policy literacy and human communication.
The core consists of: building a dependable discomfort history under time pressure; utilizing validated tools such as numerical score ranges, Wong-Baker faces for youngsters, and behavior hints for patients who can not self-report; preparing and providing anesthetics within your range; and observing, documenting, and escalating when the course deviates from plan. It is frequently bundled right into discomfort administration training courses for paramedics, event medics, initially -responders in remote market, and some severe treatment nurses, although the details pharmacology and devices differ by jurisdiction.
I have actually seen 2 pupils with the same composed scores do really in a different way when driving. The one that stood out asked another inquiry, examined one more vital indicator, and worked out with the person as opposed to treating the graph. That is the difference PUAEME008 intends to cultivate.
Pain assessment when seconds matter
An organized analysis does not suggest slow. Done well, it comes to be a pattern you can run while relocating down a hallway or packing a client right into a vehicle. Beginning by securing the basics: area, beginning, personality, intensity, radiation, organization with movement or breathing, and any kind of warnings such as syncope, lack of breath, or neurological deficits. A lot of medical professionals quit after a single numeric rating. Numbers without context mislead. A "4 out of 10" from a calm farmer with a flail upper body does not equate to a "7 out of 10" from a child with a sprained ankle.
Observe for nonverbal signs. Guarding, pallor, diaphoresis, tachycardia, modified breathing pattern, and frustration fill in spaces when a client can not provide information. For kids under 7 or for nonverbal grownups, behavior ranges are frequently much more exact than trying to force a number. PUAEME008 stresses these options, and a great discomfort monitoring program will certainly drill them till they are second nature.
Reassessment is where lots of amateurs slip. Pain rarely holds still. Movement, splinting, oxygen, or perhaps confidence can shift it. Recheck after interventions at periods established by your method, often every 5 to 10 mins at first, after that less often once secure. Record not only ball game, however the client's language. "Feels less sharp, more pressure." Those words matter, specifically when handing over.
Pharmacology within extent: choices and trade-offs
Protocols establish what you can offer. Within PUAEME008 give pain monitoring structures, the normal suspects consist of breathed in methoxyflurane, fentanyl (intranasal or intravenous), morphine, ketamine in sub-dissociative doses, laughing gas 50-50 blends, and oral representatives where time and GI standing permit. Each has pleasant places and pitfalls.
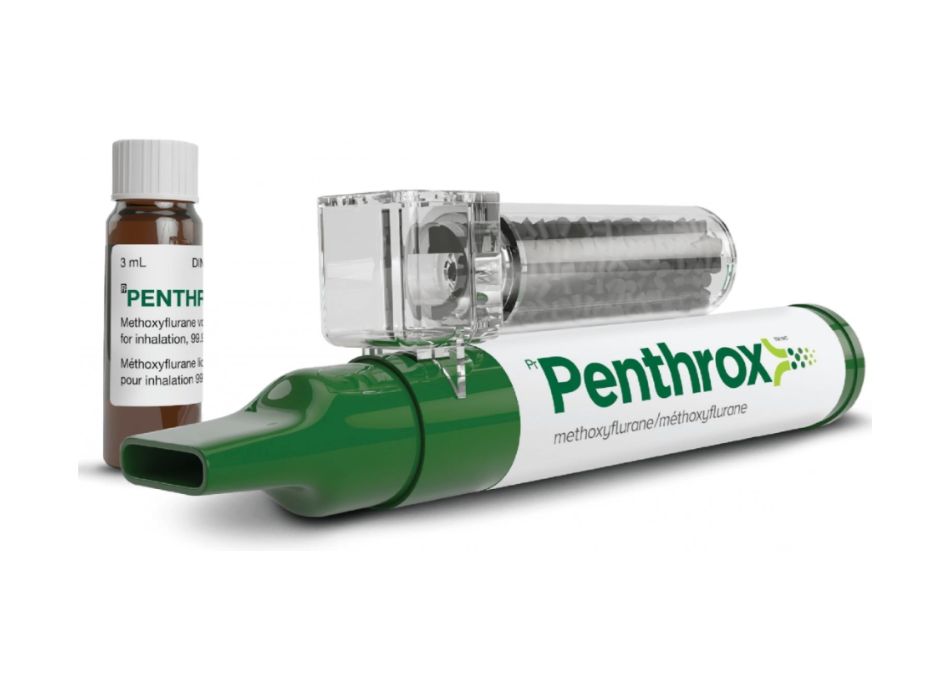
Methoxyflurane purchases time. It is rapid to provide, mobile, and well endured. I have used it on a hillside while awaiting a stretcher, its acquainted apple-pear smell a tiny comfort on a poor day. It is outstanding for moderate terrible discomfort when IV gain access to is delayed or not called for. It is less ideal for individuals with significant respiratory concession or extended administration needs.
Intranasal fentanyl is a workhorse for rapid analgesia without IV. It shines in pediatric cracks and adult limb injuries, with a clean pharmacokinetic account and simple titration. Look for breathing depression, specifically in older grownups or when combined with sedatives. Clear communication with your partner stops stacking doses as well fast.
Morphine continues to be reputable for severe pain, yet it demands cautious titration and tracking for hypotension and oversedation. I save IV morphine for clients that need sustained relief and in setups where continual surveillance is possible. It pairs well with antiemetics in individuals prone to nausea.
Sub-dissociative ketamine has expanded in popularity since it maintains respiratory tract reflexes while supplying strong analgesia and minimizing opioid demands. It can generate dysphoria or emergence sensations, which are unsettling if you have actually not prepared the client. A peaceful explanation and a calm tone decrease that risk. Ketamine likewise helps in individuals with hypotension where opioids might aggravate hemodynamics.
Nitrous oxide works and physiotherapist pain management courses acquainted in some systems, much less readily available in others. It requires individual cooperation and is badly fit to those with upper body injuries or believed pneumothorax. In the right situation, it offers fast control with marginal residual effects.
Nonpharmacological complements commonly obtain hidden under the excitement of drugs, yet they pay rewards. Splint well. Pad pressure points. Use ice bags deliberately. Adjust the setting, dark extreme lights in migraine, limitation unnecessary activity. A well-applied vacuum cleaner splint can reduce a pain rating by 2 points before any medication reaches the bloodstream.
Scope and plan: knowing the edges
PUAEME008 does not provide carte blanche. pain management certification workshops Your employer's medical instructions and regional regulations figure out which representatives and routes are permissible. The most safe clinicians are those who understand their edge instances by heart. Typical policy supports consist of minimum age limits for methoxyflurane, cumulative dosage limitations for fentanyl and morphine, contraindications for ketamine in specific psychoses or unchecked high blood pressure, and oxygen demands for nitrous oxide delivery.
When doubtful, call early for scientific appointment if your system permits it. I when managed a young adult with a femoral fracture who had actually taken unknown entertainment compounds. The blend of energizer poisoning and trauma made opioid dosing treacherous. A fast get in touch with sustained a ketamine-first approach with conservative titration and constant surveillance. Good judgment in these tight corners comes from training and from confessing unpredictability when it matters.
Communication as an analgesic
Tone changes physiology. Dignity lowers supportive drive. Basic, straightforward sentences lower fear. "You are risk-free. We are going to regulate your discomfort. You will be able to take a breath." I have actually seen discomfort scores drop a notch with those words alone.
Trust likewise safeguards against dosing mistakes. When a client thinks you are paying attention, they share vital information: last dose of oxycodone, spots on their skin, a background of opioid-induced apnea, or improperly controlled rest apnea. For older grownups, validate medication lists and ask about anticoagulants, as hemorrhaging risk can improve your functioning diagnosis and affect your option of analgesic and transport priority.
The handover seals treatment connection. A useful handover narrates: mechanism of injury or onset context, standard discomfort summary, changes after each intervention, overall dosages with timing, vitals patterns, and any side effects. A hurried recounting of numbers without arc leaves the getting group rebuilding your logic. Strong PUAEME008 training insists on that narrative clarity.
Special populations that check your craft
Pediatrics commonly daunts new clinicians. The remedy is prep work. Usage weight-based dosing graphes, keep intranasal devices within reach, and employ caretakers to hold and relax. Kids mirror grown-up anxiety. If you remain steady, they will typically clear up enough to accept splinting and intranasal analgesia without rips. Expect dehydration in prolonged abdominal discomfort, and prevent repeating intrusive attempts that can wait on a controlled environment.
Older adults provide a different puzzle. Their pain tolerance varies widely, and their physiology hides difficulty. A small fall with rib fractures can spiral into hypoventilation and pneumonia if pain is undertreated. Equilibrium efficient analgesia with loss threat and delirium prevention. Low-dose titrated opioids or ketamine, aggressive regional assistance where readily available, and early involvement of getting groups make a difference.
Pregnancy changes whatever from stomach draining to respiratory system reserve. Use left lateral tilt when viable, display fetal motions if progressed pregnancy, and select representatives with well-known security accounts in your system. Nonpharmacologic actions and regional blocks, if within range and ability, can save systemic medication exposure.
For patients with substance use conditions, think a higher standard tolerance and a greater danger of respiratory system anxiety if sedatives or alcohol get on board. Deal analgesia without judgment, however plan for air passage support. Entailing allied health early, when feasible, boosts longer-term results and decreases the rotating door effect.
When the medical diagnosis conceals under the pain
Not every agonizing discussion is a thumbs-up for full-dose opioids. Acute abdomen with vague etiology, serious frustration with neurologic adjustments, or breast pain with hemodynamic instability each calls for a deliberate pace. The old myth that analgesia covers diagnosis has been mainly unmasked, yet timing and option of agent still matter.
For suspected stomach catastrophes, moderate, titrated analgesia combined with careful review protects test energy while valuing the patient's distress. In severe migraine with red flags, treat pain while relocating promptly toward clear-cut imaging and helpful treatment, guarding against oversedation that might shadow neurologic analyses. Chest discomfort calls for synchronized analgesia and antiplatelet or anticoagulant treatment per protocol, together with rhythm tracking and nitrates if shown. Good care lives in combination, not on single-track thinking.
Training that adjustments just how you practice
The finest pain administration training courses build muscular tissue memory under realistic restraints. Manikins and instance scenarios work, however absolutely nothing replaces online, unpleasant method: deciding dosing while the blood pressure alarm tweets, mentoring breathing with contractions while a second patient calls your name, or weighing the risks of an additional fentanyl aliquot in a person whose oxygen saturation just dipped.
When picking a discomfort management certification program, try to find programs that combine:
- Scenario-based simulations that require prioritization, review, and handover under time pressure Pharmacology sessions that show system, communications, and unfavorable event administration, not simply dosing tables
Assessment needs to be more than a created test. Proficiency demos, medicine prep work drills, damaging event acknowledgment, and communication circumstances expose whether learning translates to activity. For nurses branching right into immediate treatment or access atmospheres, pain management training courses for registered nurses that integrate PUAEME008 expertises with triage systems and local formularies supply the best worth. Physio therapists operating in acute musculoskeletal settings additionally benefit from discomfort management training courses for physiotherapists that highlight nonpharmacologic techniques along with interdisciplinary coordination; if pharmacologic administration is out of extent, the training must still cover acknowledgment of undertreatment and rise pathways.
Short courses hurting management can be worthwhile, yet examine that "short" does not suggest shallow. A concentrated one-day program can provide targeted skills, for example, intranasal analgesia in pediatric medicines or ketamine titration for injury, supplied it consists of supervised practice and post-course mentoring. A certification program hurting monitoring that assures wide capacity needs to include monitored professional time or durable simulation to validate a discomfort administration certification.
Documentation secures people and clinicians
No one takes pleasure in documentation in the warmth of method, but a clean document belongs to the treatment. It informs the following clinician what functioned and what did not, it protects the patient from duplicated application, and it shields you when outcomes are examined days later.
Elements to tape consist of the baseline discomfort summary, objective indications, the rationale for representative choice, dose and time, route, individual response, vitals trends, negative events and reduction, and the material of the handover. If you deviated from a conventional series as a result of a patient-specific aspect, write the reason in a total sentence. That habit constructs count on your scientific judgment.

Building a culture of prompt analgesia
Individuals can exercise well, yet systems still fall short people if society punishes analgesia as high-risk or optional. I have actually worked in solutions where discomfort relief required 3 trademarks, and the predictable outcome was experiencing. It took a data-driven argument to alter minds: time to initial analgesia stopped by 40 percent after procedure simplification, and there was no rise in respiratory system compromise when monitoring standards were maintained. The management then ingrained analgesia metrics into quality control panels, and the society shifted.
If you are in a position to influence policy, supporter for simple access to approved representatives, standardized checklists for prep work and tracking, and routine case evaluates that concentrate on discovering as opposed to blame. Connection pain metrics to client experience comments, not as a score to chase after thoughtlessly, but as one vital sign of thoughtful care.
Practical ideas from the field
Over years of teaching PUAEME008 offer pain monitoring, a couple of tiny habits maintain paying off.
- Prime your set for the very first 10 mins. Maintain intranasal atomizers preloaded and labeled by dosage array, methoxyflurane accessible, and tape pre-cut for splints. The faster you can act, the cleaner your decision-making.
Practice a dose-talk script. Patients and households kick back when they hear positive, regular descriptions: name the drug, anticipated benefits, usual side effects, and what you will certainly do to monitor.
Think in pairs. One clinician prepares and provides, the various other watches respiratory tract, air flow, and psychological standing. Also in a tiny team, assign roles clearly for risky moments.
Use the pain range as a conversation starter, not a decision. Ask what number would certainly allow them move or take a breath more comfortably, then aim for that target as opposed to zero.
Plan the following step before you supply the current one. If this dosage does not function, what is your second line, what are the contraindications, and when will certainly you reassess?
Those micro-skills make the difference in between positive care and disorderly improvisation.
Where PUAEME008 fits amongst broader certifications
Many medical professionals collect badges, and not all badges convert to better care. A discomfort management certification shows you have met a standard, but continuous proficiency originates from purposeful technique. If you are thinking about a pain monitoring accreditation course, align it with your work environment. Prehospital medical professionals benefit from programs linked to actual operational medication listings, tools, and paperwork systems. Hospital-based staff could like components that cover nerve blocks, infusion pumps, and multimodal analgesia pathways.
For nurses in immediate care or ED triage roles, pain management training for nurses that mixes pharmacology, injury assessment, and interaction training enhances both throughput and client fulfillment. For allied health specialists, a discomfort administration certification training course can clear up borders and rise paths, avoiding unsafe delays when pharmacologic pain control is appropriate.
The highest-yield programs close the loophole with mentorship. A solitary day of lectures does not alter reflexes. A month of on-shift mentoring does.
Measuring success beyond the pain score
Pain scores relocate the needle, however they are not the only end result worth monitoring. I look for less unscheduled returns as a result of inadequate analgesia, much shorter time to mobilization in easy fractures, lower incidence of oxygen desaturation throughout opioid use, and much better handover clarity. Client comments inform you greater than study numerics. If individuals state feeling heard, safe, and sustained, your analgesia technique is likely sound.
Systems that installed PUAEME008 requirements see downstream gains in sedation safety, lowered frustration throughout transportation, and tighter team effort. Those gains compound. Much less mayhem indicates fewer mistakes, and fewer mistakes imply more power for the following individual that requires your ideal judgment.
Final ideas from the sharp end
Pain is a clinical problem and an ethical one. When somebody counts on you with their suffering, they are not requesting heroics. They are requesting for attention, ability, and follow-through. PUAEME008 orders that contract into competencies you can practice, examination, and refine.
If you are choosing amongst discomfort management training programs, choose the one that demands your presence, not simply your presence. Ask just how they instruct emergency situation pain administration under realistic constraints, how they evaluate communication, and just how they maintain your abilities to life after the certificate is framed. Whether you are discovering a provide pain management program as your first step or including a discomfort monitoring accreditation to a recognized profession, treat the system as the start of a behavior: analyze with interest, treat with precision, and circle back to see if you genuinely helped.
The days that stick with me are not the huge saves. They are the quiet success, like the distressed youngster that was giggling by the time we reached radiology because someone took 5 additional minutes to discuss the intranasal spray and hold a hand. That is the basic worth training for, and the pledge behind any kind of training course that asserts to teach discomfort well.
